Acanthosis Nigricans Revealing Underlying Insulin Resistance in a Young Adult
OthersPage Navigation
Introduction
Acanthosis nigricans is characterised by symmetrical, hyperpigmented, thickened, and velvety plaques. It commonly affects the neck, axillae, groin, and other flexural areas. It represents a clinical reaction pattern rather than a single disease and may be associated with obesity, insulin resistance, endocrine disorders, medications, genetic conditions, or, less commonly, internal malignancy.
In adolescents and adults, acanthosis nigricans frequently serves as an external marker of hyperinsulinaemia and cardiometabolic risk. Because the lesions may be mistaken for retained dirt or ordinary pigmentation, patients may repeatedly scrub the skin, leading to irritation and delayed medical evaluation.
Clinical assessment should consider the onset, progression, distribution, associated symptoms, medication exposure, weight pattern, and features suggestive of endocrine disease or malignancy. Management primarily focuses on identifying and treating the underlying cause.
Case Report
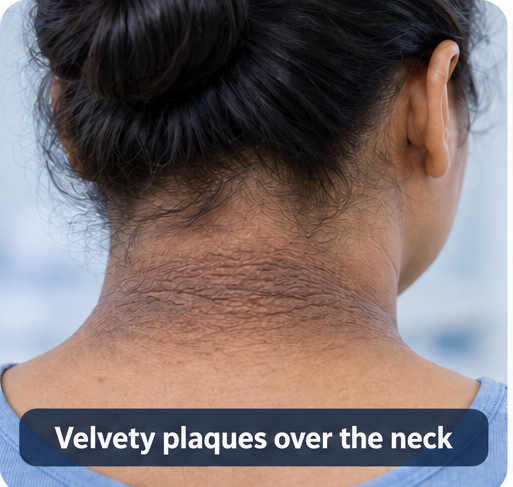
A 28-year-old woman presented with gradually increasing darkening and thickening of the skin over the back and sides of her neck for approximately eighteen months.
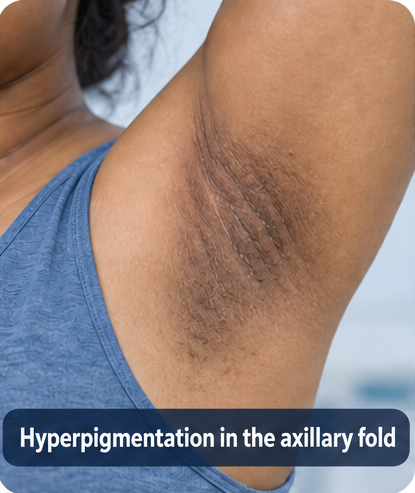
Similar but less prominent changes had developed in both axillae during the preceding six months.
She described the affected skin as rough and difficult to clean. Repeated washing and vigorous scrubbing caused temporary redness but did not improve the pigmentation. The lesions were generally asymptomatic, apart from occasional mild irritation caused by friction.
During the previous three years, she had gained approximately 12 kg. She reported limited physical activity and frequent consumption of energy-dense snacks and sweetened beverages. Her menstrual cycles occurred every 35–45 days.
She denied excessive hair growth, severe acne, galactorrhoea, heat or cold intolerance, proximal muscle weakness, easy bruising, or prolonged corticosteroid use.
She had no previously diagnosed diabetes mellitus or hypertension. Her mother had type 2 diabetes mellitus. There was no history of unexplained weight loss, reduced appetite, persistent gastrointestinal symptoms, oral lesions, or gastrointestinal malignancy in the family.
She was not taking insulin, nicotinic acid, hormonal therapy, or other medication commonly associated with acanthosis nigricans.
On examination, her weight was 82 kg and height was 1.62 m, corresponding to a body mass index of 31.2 kg/m². Her waist circumference was 96 cm, and blood pressure was 128/82 mmHg.
Dermatological examination revealed symmetrical, poorly demarcated, brown-grey, velvety plaques with accentuated skin markings over the posterior and lateral neck. Similar changes were present in both axillae. Several small skin tags were also observed around the neck.
There was no erythema, scaling, maceration, tenderness, discharge, odour, or mucosal involvement.
The gradual onset, characteristic flexural distribution, obesity, and family history of diabetes suggested obesity-associated acanthosis nigricans with underlying insulin resistance.
Investigations
Fasting plasma glucose was 112 mg/dL, while glycated haemoglobin was 6.1%, indicating prediabetes. Fasting insulin was elevated at 27 µIU/mL.

The calculated homeostatic model assessment of insulin resistance was approximately 7.5, supporting significant insulin resistance in the appropriate clinical context.
The lipid profile showed:
- Triglycerides: 196 mg/dL
- High-density lipoprotein cholesterol: 38 mg/dL
- Low-density lipoprotein cholesterol: 126 mg/dL
Alanine aminotransferase was mildly elevated at 48 U/L. Other liver-function parameters were within reference ranges.
Thyroid-stimulating hormone was 2.4 mIU/L. Serum creatinine and complete blood count were normal. A pregnancy test was negative.
Because menstrual irregularity was present, further evaluation for polycystic ovary syndrome was advised. However, the patient did not have marked hirsutism, inflammatory acne, or virilisation on examination.
Abdominal ultrasonography demonstrated mild hepatic steatosis without any focal lesion.
The diagnosis was clinical. Skin biopsy was not considered necessary because the morphology and distribution were characteristic and no atypical features were present.
Differential Diagnosis
Confluent and Reticulated Papillomatosis
This condition may produce hyperpigmented papillomatous lesions over the neck and upper trunk. However, the absence of a reticulated peripheral pattern and the presence of typical velvety plaques in major flexural areas favoured acanthosis nigricans.
Terra Firma-Forme Dermatosis
Terra firma-forme dermatosis may resemble dirty-appearing hyperpigmentation that persists despite routine washing. However, the lesions in this patient showed palpable velvety thickening and a symmetrical flexural distribution.
Post-Inflammatory Hyperpigmentation
There was no history of a preceding inflammatory eruption. Post-inflammatory pigmentation would also not adequately explain the characteristic papillomatous texture and accentuated skin markings.
Erythrasma or Intertrigo
These conditions were considered less likely because there was no erythema, scaling, maceration, tenderness, or odour. The neck involvement was also clinically characteristic of acanthosis nigricans.
Malignant Acanthosis Nigricans
The patient had gradual, limited flexural involvement without mucosal lesions, marked pruritus, tripe palms, unexplained weight loss, or systemic symptoms. A malignant association was therefore considered unlikely.
Rapid onset, extensive progression, mucosal involvement, marked pruritus, tripe palms, or constitutional symptoms would have prompted urgent investigation for an underlying malignancy.
Management and Outcome
The patient was informed that the pigmentation was not caused by poor hygiene and that vigorous scrubbing could worsen irritation.
The association between the skin findings, excess body weight, hyperinsulinaemia, and future cardiometabolic risk was explained using non-stigmatising language.
A structured lifestyle-management programme was initiated, including dietary counselling, gradual calorie reduction, avoidance of sweetened beverages, and progressive aerobic and resistance exercise.
Realistic weight-loss and waist-circumference goals were established. Because laboratory investigations showed prediabetes and marked insulin resistance, the patient was referred to an endocrinologist for comprehensive metabolic management.

Following clinical evaluation and confirmation that no contraindications were present, metformin was initiated at a low dose and gradually adjusted according to tolerance as part of the management of the underlying metabolic abnormality.
For the neck lesions, a topical keratolytic moisturiser was prescribed. She was advised to avoid aggressive rubbing and discontinue the topical treatment if significant irritation developed.
The patient was informed that improvement in pigmentation would occur gradually and might lag behind improvement in metabolic parameters.
At the three-month follow-up, she had lost 5.2 kg, and her waist circumference had decreased by 6 cm. Fasting plasma glucose had fallen to 101 mg/dL. She reported improved energy levels and regular participation in physical activity.
The plaques remained visible but appeared less thick and less prominent. No new anatomical areas were involved.
At six months, her total weight loss was 8.4 kg. Glycated haemoglobin had decreased to 5.7%, and triglyceride levels had improved. The neck plaques showed further flattening and lightening.
She continued coordinated dermatological and metabolic follow-up.
Discussion
This case illustrates how a common dermatological finding may reveal previously unrecognised metabolic risk. Acanthosis nigricans is usually diagnosed clinically through its characteristic velvety thickening and hyperpigmentation in flexural areas.
Histopathological examination may support the diagnosis when the morphology is atypical, but a routine biopsy is generally unnecessary in a classic clinical presentation.
In obesity-associated acanthosis nigricans, compensatory hyperinsulinaemia is believed to stimulate keratinocyte and fibroblast proliferation through growth-factor pathways.
The visible severity of the lesions does not provide a precise measurement of insulin resistance. Nevertheless, their presence should prompt an assessment of body-weight pattern, waist circumference, blood pressure, glucose regulation, lipid levels, family history, and other features of metabolic syndrome.
The clinical history also helps distinguish common metabolic acanthosis nigricans from less common but clinically important causes. Medication exposure should be reviewed, while accompanying endocrine features may guide testing for polycystic ovary syndrome, thyroid dysfunction, or glucocorticoid excess.
Sudden onset, rapid progression, extensive or atypical lesions, marked pruritus, mucosal involvement, tripe palms, or constitutional symptoms should raise concern for malignant acanthosis nigricans and prompt targeted investigation.
Treatment is most effective when directed towards the underlying cause. Weight reduction and improved insulin sensitivity may reduce lesion thickness and pigmentation, although cutaneous improvement can be gradual and incomplete.
Metformin may be considered when clinically indicated for an underlying metabolic disorder but should not be presented as a purely cosmetic treatment. Topical keratolytic agents or retinoids may be considered for persistent lesions, depending on the affected site, patient preference, and risk of irritation.
Counselling is equally important. Patients may mistakenly believe that the darkened skin results from inadequate washing. Explaining the biological basis of the condition can reduce stigma and discourage potentially harmful attempts to scrub or bleach the skin.
Conclusion
Acanthosis nigricans should be recognised as a clinical clue rather than an isolated pigmentary disorder.
In this young adult, characteristic flexural plaques led to the identification of obesity-associated insulin resistance, prediabetes, dyslipidaemia, and early fatty liver changes.
Focused evaluation, respectful counselling, lifestyle modification, and coordinated management of the underlying metabolic risk resulted in measurable metabolic improvement and gradual regression of the skin lesions.
Atypical, extensive, or rapidly progressive presentations require a broader evaluation for medication-related, endocrine, genetic, or malignant causes.
References
- Phiske MM. An approach to acanthosis nigricans. Indian Dermatology Online Journal. 2014;5(3):239–249. https://pmc.ncbi.nlm.nih.gov/articles/PMC4144206/
- Videira-Silva A, Albuquerque C, Fonseca H. Acanthosis nigricans as a clinical marker of insulin resistance among overweight adolescents. Annals of Pediatric Endocrinology & Metabolism. 2019;24(2):99–103. https://pmc.ncbi.nlm.nih.gov/articles/PMC6603613/
- Popa ML, Popa AC, Tanase C, Gheorghisan-Galateanu AA. Acanthosis nigricans: To be or not to be afraid. Oncology Letters. 2019;17(5):4133–4138. https://pmc.ncbi.nlm.nih.gov/articles/PMC6444334/
- Patel NU, Roach C, Alinia H, Huang WW, Feldman SR. Current treatment options for acanthosis nigricans. Clinical, Cosmetic and Investigational Dermatology. 2018;11:407–413. https://www.dovepress.com/current-treatment-options-for-acanthosis-nigricans-peer-reviewed-fulltext-article-CCID
- Radu AM, Carsote M, Dumitrascu MC, Sandru F. Acanthosis nigricans: Pointer of endocrine entities. Diagnostics. 2022;12(10):2519. https://www.mdpi.com/2075-4418/12/10/251
Read more such content on @ Hidoc Dr | Medical Learning App for Doctors
Recommended News For You
Recommended Articles For You
Featured News
Featured Articles
Featured Events
Featured KOL Videos
1.
For MDS-Related Anemia, Telomerase Inhibitor Approved.
2.
Efficacy and safety of intravenous chemotherapy in children with intraocular retinoblastoma
3.
Admissions, medical schools, costs, and eligibility requirements information for FNB Onco-Anesthesia.
4.
Treating Depression: Crucial for Recovery From Fibromyalgia
5.
In postmenopausal women with hormone receptor-positive tumors, obesity increases the risk of breast cancer recurrence.
1.
Empowering Oncology with Data: Cloud Security, Real-World Evidence, and Clinical Insights
2.
Immune Regulation of Blood Cell Development
3.
Exploring the Effects of Radiation Therapy on Cystitis: A Journey to Better Health
4.
Transformative Frameworks in Oncology for Better Care
5.
Liposomal Doxorubicin and Mitomycin in Modern Cancer Treatment
1.
International Conference on Oncology, Cancer Prevention and Public Health
2.
International Conference on Cancer Nursing and Rehabilitation Strategies
3.
International Conference on Best Practices in Oncology, Cardiology and Critical Care
4.
International Conference on Innovations in Critical Care for Oncology and Cardiology
5.
International Symposium on Oncology, Cardiology and Critical Care Innovations
1.
Targeting Oncologic Drivers: A New Approach to Lung Cancer Treatment
2.
Newer Immunotherapies for Myeloma- A Comprehensive Overview
3.
Understanding the causes of anemia in adults beyond nutritional deficiencies
4.
Revolutionizing Treatment of ALK Rearranged NSCLC with Lorlatinib - Part III
5.
Guideline Recommendations of Lorlatinib as First-Line Treatment for ALK+ NSCLC

Address :
Hidoc Dr. Inc. | Delaware C Corp | 1309 Coffeen Ave. Suite 1200, Sheridan WY, 82801
Phone :
+1-415-463-3094
Email :
anishagadia@hidoc.co
© Copyright 2026 Hidoc Dr. Inc.
Terms & Conditions - LLP | Inc. | Privacy Policy - LLP | Inc. | Account Deactivation

To get started please enter your email ID
Welcome to Hidoc Dr.
Join to enhance your clinical skills and gain specialized in-depth medical knowledge