Congenital Heart Disease In Children
All SpecialityPage Navigation
ABSTRACT
Congenital heart disease (CHD) is the most common congenital disorder in neonates.
A number of factors including genetic factors, teratogenic exposure and several other unrecognised factors have been associated with its development.
Ventricular Septal Defect (VSD) is the most common type.
INTRODUCTION-
Congenital Heart Defects are structural abnormalities of heart and/or great blood vessels during fetal development.
CHDs account for about 28% of all congenital anomalies. It is a result of lack of normal development of heart during the embryonic phase.
Prevalence- 1% births in the United States.
1.5-1.7/1000 live births in India.
ETIOLOGY –
Mostly unknown.
Sometimes associated with –
• Chromosomal abnormalities and Genetic disorders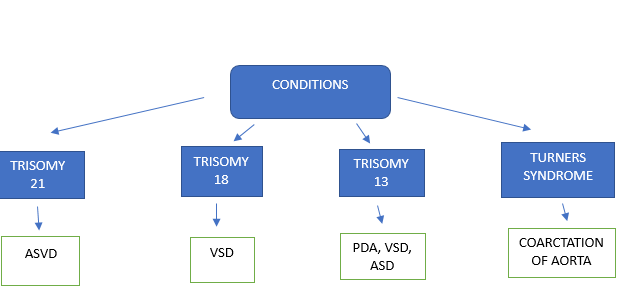
• Teratogenic factors including maternal smoking, alcohol abuse, exposure to retinoid, indomethacin, tocolytics.
• Maternal infection with rubella.
• Additionally, history of epilepsy in mother, phenylketonuria, maternal age above 30, Type 1 and Type 2 DM as well as positive family history are other risk factors.
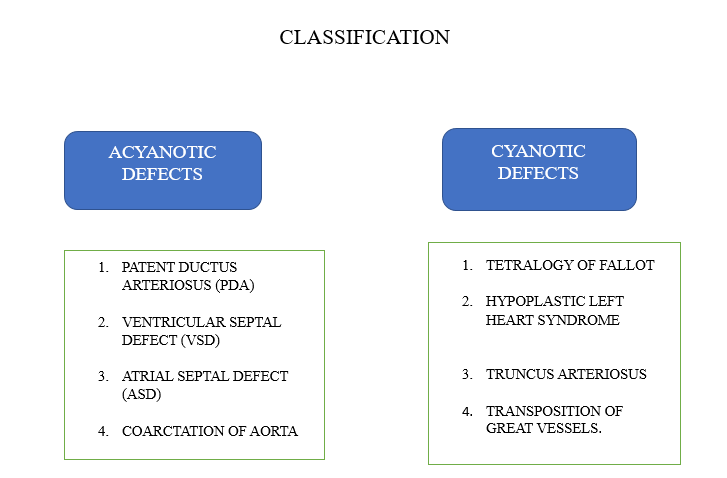
ASD –
• Abnormal opening in the septum between right and left atrium.
• Normally L to R shunt.
• Most common type is secundum ASD (80%).
• Wide fixed split s2 is the pathognomic for ASD.
• Clinical manifestations are non-specific.
VSD –
• Defect in interventricular septum.
• Shunting of blood from L to R.
• Most common type is peri membranous.
• Holosystolic/ high pitched murmur
• Small VSDs are usually asymptomatic. Moderate VSDs can cause frequent respiratory infections and fatigue.
• Larger VSD can lead to reversal of shunt in Eisenmenger syndrome.
TETRAOGY OF FALLOT –
• 4 Defects are present in the heart
1) Right ventricular outflow obstruction
2) Right ventricular hypertrophy
3) Overriding aorta
4) Ventricular septal defect
• Clinical manifestations include cyanosis, tachypnoea, “tet spells”
• Harsh systolic ejection murmur (best heard at left sternal border)
• Boot shaped heart on CXR.
• Surgical repair definitive
COARCTATION OF AORTA –
• Narrowing of the descending aorta typically located at the insertion point of the ductus arteriosus, just distal to the left subclavian artery
• Often associated with bicuspid aortic valve and turners syndrome
• Posterior rib notching and figure 3 sign on CXR.
PATENT DUCTUS ARTERIOSUS –
• Condition in which ductus arteriosus (small artery which connects fetal pulmonary artery to aorta) remains patent and does not close after birth.
• Epidemiology –
1. Prematurity
2. 2:1 female predominance
3. Higher altitude
4. Congenital rubella
• Caused from continual prostaglandin E1 production
• Continuous machine-like murmur and bounding peripheral pulses on physical exam.
PREVENTION –
Prevention of congenital anomalies is important as the impact can be for life. Environmental factors known to be the risk factors in etiology need to be suitably addressed. First approach should be for families with children or relatives with CHD. Second, environmental factors need to be suitably addressed.
DETECTION AND DIAGNOSIS-
Early detection is desirable. The suspicion of CHD is mainly clinical. Evaluation should be done on the basis of Nadas’ criteria for diagnosis of CHD.
The major criteria include -
1. Systolic murmur grade 3 or more
2. Diastolic murmur
3. Cyanosis
4. Congestive cardiac failure
The minor criteria include –
1. Abnormal echo
2. Abnormal X ray
3. Abnormal BP
Presence of 1 major or 2 minor criteria indicates heart disease.
In infants, feeding difficulties are common. Others include poor weight gain, irritability, breathing difficulty, inappropriate sweating and persistent cough.
Read more such content on @ Hidoc Dr | Medical Learning App for Doctors
Recommended News For You
Recommended Articles For You
Featured News
Featured Articles
Featured Events
Featured KOL Videos
1.
Durvalumab Plus BCG Earns FDA Nod for Bladder Cancer
2.
GLP-1 receptor agonists show anti-cancer benefits beyond weight loss
3.
MGRS Relapse-Free Survival Better With Maintenance Therapy
4.
New protein target discovered for childhood medulloblastomas
5.
The pancreatic ductal adenocarcinoma mRNA vaccine holds promise for preventing relapse.
1.
Essential Updates in Hematology in Daily Practice
2.
Engineering the Future of Oncology with CAR- Natural Killer Cell Design & Therapeutics
3.
A Visual Journey Through Penile Cancer: Examining the Impact of Photos
4.
Potential of Device-Assisted Therapy in Non-Muscle-Invasive Bladder Cancer
5.
The Silent Danger of Hematoma: How to Identify and Treat This Potentially Serious Condition
1.
International Conference on Best Practices in Oncology, Cardiology and Critical Care
2.
International Conference on Innovations in Critical Care for Oncology and Cardiology
3.
International Symposium on Oncology, Cardiology and Critical Care Innovations
4.
International Conference on Cancer Nursing and Hematology Support
5.
International Conference on Clinical Medicine and Surgical Care
1.
Understanding Common Causes of Abnormal Blood Counts
2.
Role of Nimotuzumab in Management of Nasopharyngeal Cancer
3.
Understanding Blood Disorders and Their Diagnosis
4.
Managing ALK Rearranged Non-Small Cell Lung Cancer with Lorlatinib - Part II
5.
Unmet Needs in ALK Positive NSCLC- The Challenges in the Current Care

Address :
Hidoc Dr. Inc. | Delaware C Corp | 1309 Coffeen Ave. Suite 1200, Sheridan WY, 82801
Phone :
+1-415-463-3094
Email :
anishagadia@hidoc.co
© Copyright 2026 Hidoc Dr. Inc.
Terms & Conditions - LLP | Inc. | Privacy Policy - LLP | Inc. | Account Deactivation

To get started please enter your email ID
Welcome to Hidoc Dr.
Join to enhance your clinical skills and gain specialized in-depth medical knowledge